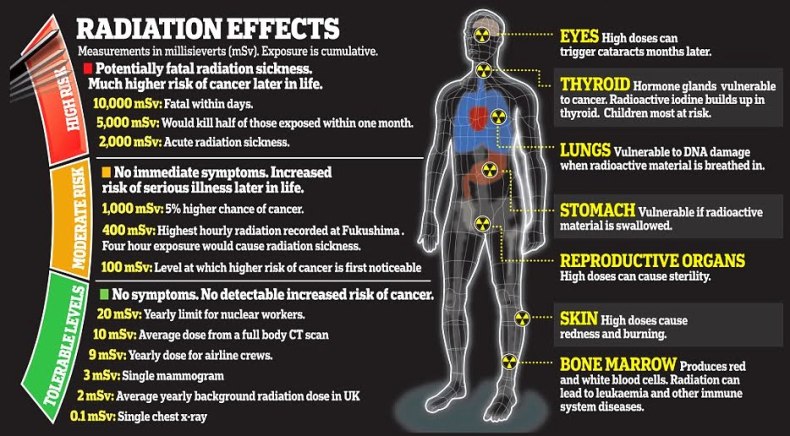
Kristin Shrader-Frechette: Millions of US children receive X-rays each year, but university physicians recently discovered that radiation doses as low as 1 to 5 millisievert may give these children small, but statistically significant, increased risks of cancer. (A millisievert measures the biological effect of ionizing radiation on human tissue.).
However, the annual allowed public dose from each nuclear facility in the United States is 1 to 5 millisievert. Because even a dose of 1 to 5 millisieverts likely increases cancer risks, and at least 70 percent of US reactors have released radioactivity that violates health standards, should populations near nuclear facilities be tested?
Bulletin of Atomic Scientists 21st May 2026, May 2026
New research finds correlation between disease and living close to a facility
HARVARD GRIFFIN GSAS NEWS, By Kaitlyn Hung, May 19, 2026
uclear power accounts for 18 to 20 percent of electricity generated in the United States. In some places, the share is much greater—over half the energy generated in Illinois, for instance, the country’s sixth-largest state. As demand rises sharply, particularly from AI data centers, the federal government has increased funding, loans, and tax incentives in an effort to increase nuclear capacity, extend operations of existing reactors, and restart retired ones.
Although public support for nuclear energy has surged in recent years, opposition remains strong. The most common reason? Safety concerns. And they may be valid, according to population health scientist Yazan Alwadi, who received his PhD from the Harvard Kenneth C. Griffin Graduate School of Arts and Sciences in February 2026, months after receiving a master’s degree in biostatistics in November 2025. Now a post-doctoral researcher at the Harvard T.H. Chan School of Public Health, Alwadi’s work uncovers a link between cancer and proximity to nuclear power plants.
Too Close for Comfort?
In the lab of Petros Koutrakis, Akira Yamaguchi Professor of Environmental Health and Human Habitation at the T.H. Chan School, Alwadi investigated whether living close to nuclear facilities impacts a population’s incidence of developing or dying from cancer. The work was motivated by a call from the Department of Public Health in Plymouth County, Massachusetts. Community members were concerned about rising cancer cases, and some wondered whether Plymouth’s Pilgrim Nuclear Power Station, decommissioned in 2019, might have contributed to the uptick.
“We get emails from families, saying that big percentages of people they know get cancer. But of course, these are anecdotal, so it needs hard science and statistical evidence to see if that actually happens or not,” Alwadi says.
As an environmental epidemiologist, Alwadi decided to investigate. “We wanted to know, are we going to find an association between the proximity to plants and cancer or not?” Alwadi says. Regardless of the outcome, he would share his findings.
Alwadi conducted a longitudinal ecological study, comparing Massachusetts zip codes’ proximity to the seven nuclear facilities in the vicinity of the state with that zip codes’ cancer incidence over time (provided by the state’s cancer registry). He used proximity as a proxy for exposure because it encompasses multiple routes of dispersal, like air and water. “We know that distance is a proxy for most [exposure routes]. It’s not perfect for any one of them, but a proxy for most,” Alwadi says.
Alwadi discovered a strong association between cancer incidence and proximity to plants for populations over 55 years old living within 5 km of a nuclear power plant. For example, women ages 65-74 living two km away from a nuclear power plant had 2-times higher relative risk of cancer, and men in this age group had 1.75-times higher risk.
To determine whether these results were more broadly generalizable to the United States, Alwadi conducted a similar study comparing nuclear power plant proximity to county-level data on cancer mortality from the US Centers for Disease Control. “We felt that doing [the analysis] nationally would give us enough statistical power to depict effects if they truly exist,” says Alwadi. He discovered that the association he observed in Massachusetts held at the national level, too. “We observe the same association, similar values, same decline of risks with distance across different aggregations, zip codes versus counties . . . for cancers of interest.”
Koutrakis says that his advisee’s research is notable because it is the first series of studies to systematically demonstrate associations between residential proximity to nuclear power plants and cancer outcomes across multiple settings using large, population-based datasets. “This work fills a critical gap in the literature by providing large-scale, systematic evidence on a question that has remained unresolved for decades.” …………………………………………….
Importantly, while the study shows a robust association between nuclear plant proximity and cancer, the study’s design cannot determine whether that relationship is causal. “Although these are ecological designs that do not establish causality and are very hard to infer causality from their evidence, the systematic results and the consistency of the findings are exactly what you’d expect to find if a true underlying causal effect existed,” says Alwadi. By systematically demonstrating an association, Alwadi’s discovery provides the impetus for more detailed research to understand the nature of the link between nuclear power plants and cancer. ………………………………………………………………………………………………………………………………………………………….
………………………………………………… Digging Deeper
Since graduation, Alwadi has continued his work in the Koutrakis lab as a postdoctoral fellow. Today, he tracks the relationship between nuclear facility proximity and cancer within individuals, rather than populations. He says this cohort analysis will provide stronger evidence for the nature of the association by reducing bias and clarifying the temporality of nuclear facility exposure to cancer development.
Ultimately, Alwadi hopes to lead a lab of his own in environmental epidemiology and public health. He’s got a plethora of questions he wants to tackle, so to him, it’s just a matter of time and resources to get the work done. “We see a signal, we keep digging,” he says. https://gsas.harvard.edu/news/does-proximity-nuclear-power-plants-increase-cancer-risk
This national-scale analysis provides new evidence that proximity to nuclear power plants is associated with increased mortality from major cancers in the U.S. The magnitude and consistency of the findings highlight the importance of updated risk assessments, sustained surveillance, and strengthened public health planning for communities living near nuclear facilities.
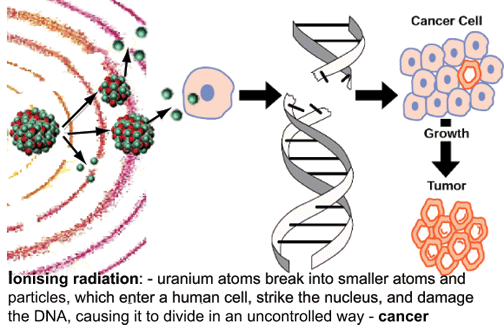
Nuclear power plants emit low levels of ionizing radiation, an established risk factor for breast, colon, and lung cancers, yet the long-term effects of chronic environmental exposure in U.S. populations remain unclear.
Objective
To evaluate sex- and age-specific associations between proximity to nuclear power plants and mortality from the three most common cancers in the U.S.: breast, colon, and lung cancer.
Methods
We quantified county-level proximity to nuclear power plants using the sum of inverse distances from each residence county’s population-weighted center to all plants within 200 km, updated annually from 2000 to 2020. Cancer-specific mortality data (breast, colon, and lung) from the CDC were analyzed by sex and five age groups (45–54, 55–64, 65–74, 75–84, 85 + ). Relative risks (RRs) were estimated using generalized estimating equations with a Poisson link. Models were adjusted for sociodemographic factors, urbanicity, region, and temporal trends.
Results
Proximity to nuclear power plants was associated with elevated mortality from breast, colon, and lung cancers. From 2000 to 2020, an estimated 39,767 female deaths (95% CI: 9312–69,381), representing 2.01% (95% CI: 0.47–3.50%), and 38,124 male deaths (95% CI: 16,106–59,600), representing 2.33% (95% CI: 0.98–3.64%), were attributable to this proximity. Lung cancer accounted for the largest burden in both sexes, followed by breast and colon cancer in females and colon cancer in males. Mortality risks declined with increasing distance, becoming negligible beyond 50 km.
Significance
This national-scale analysis provides new evidence that proximity to nuclear power plants is associated with increased mortality from major cancers in the U.S. The magnitude and consistency of the findings highlight the importance of updated risk assessments, sustained surveillance, and strengthened public health planning for communities living near nuclear facilities.
Impact
This study provides the first national assessment of sex- and age-specific mortality from breast, colon, and lung cancers in relation to proximity to U.S. nuclear power plants, revealing consistent patterns not previously demonstrated. These findings fill a major gap in environmental epidemiology and underscore the need for cohort studies, refined exposure assessments, and pathway-specific analyses to strengthen causal interpretation. As nuclear power gains momentum in national energy planning, establishing clearer evidence on potential health impacts is increasingly essential for guiding research priorities and public health preparedness.
Changes for worse or better protection for workers and the public is on the international and national political agenda in a number of countries. Trade Union, environment and public health groups around the world are concerned that the USA is considering proposals that would weaken radiation protection standards at a time when the scientific evidence suggests these need to be significantly tightened.
Our concern arises as a result of a Directive (EO 14300) 1 issued in May 2025 by US President Donald Trump requiring the US Nuclear Regulatory Commission (NRC) to review nuclear safety regulations with particular reference to radiation protection of workers and the public. The Directive instructs the NRC to abandon fundamental principles that have formed the basis for radiation protection for much of the past century. These include: the internationally accepted position that there is no threshold or safe level of exposure; that, as a consequence, all exposures should be kept as low as reasonably achievable (ALARA) ; and all exposures to workers and the public be kept below strict annual limits in line with the best evidence of radiation-induced health risks.
The evidence used to set current standards was drawn mainly from the studies of cancer rates among the Japanese A-bomb survivors who were exposed to relatively high doses over short time periods. Since then studies of workers in nuclear power facilities exposed to lower doses over long time periods show higher rates of cancer than predicted by the Japanese studies. Rather than indicating any threshold these studies suggest that at low doses the cancer rates are proportionately higher than expected from the Linear No- Threshold model used to set current standards. 2 Worker studies also show elevated rates of cardio-vascular diseases 3 , and increased rates of dementia 4 . In addition, studies on populations around nuclear power plants are now showing higher cancer rates affecting particularly children 5 and the elderly 6 – correlated to how close they lived to these facilities. Despite this mounting evidence that exposure limits should be lowered the likely result of changes in line with the Presidential directive would be to increase the permissible exposure limit for workers and the public to five times the current internationally recommended level.
The US NRC is clearly faced with a dilemma. To adopt the changes demanded by the President would require reversing its 2021 decision that specifically rejected these same proposals 7 . The initial date for publication of the NRC’s draft response for public consultation was 23 February 2026. This was deferred to 30 April and again at short notice to 24 June. One might speculate that despite large scale resignations and lay-offs among NRC staff there remain some with scientific integrity opposing the changes. However the final revision of standards is required by end of November 2026. Given the President’s record for seeking retribution on government representatives or officials who oppose his plans it is hard to see any outcome from the NRC other than a change to weaken the US standards.
There will also likely be pressure on international and national standards agencies to align with changes in the USA. Some push-back can be expected. Already the heads of European standards agencies have issued a statement supporting the LNT and ALARA principles and insisted that exposure standards be set on the basis of the scientific evidence without undue influence. 8 However NRC changes in line with the Trump Presidential Directive will embolden the nuclear power lobby and create pressure for change where there are joint ventures involving US military or industrial interests. These changes are also likely to impede public pressure for review and improvement of current standards.
In Australia, for example, there are a number of joint ventures in uranium and radioactive rare earths and mineral sands mining and the government has already established a separate Naval Nuclear Power Safety Regulator (ANNPSR)to oversee all aspects of construction, operation, maintenance, decommissioning and nuclear waste management under the Australia-UK-US (AUKUS) nuclear submarine program. While these standards are expected to be consistent with those of the current Australian Radiation and Nuclear Safety Agency (ARPANSA) the pressure for change can come from either agency. Hopefully it will be politically independent science-based pressure to not merely oppose the direction prompted by the US President’s directive but for better standards to protect health of workers and the public where they are routinely exposed to ionising radiation.
The two Diablo Canyon nuclear reactors in San Luis Obispo County CA began operations in 1984 and 1985. They have generated enormous amounts of highly radioactive waste. Most is stored at the site, but some is routinely released into the environment – and into humans through breathing, food, and water. However, no studies on health effects to the local population have been done.
Exposure to radiation is especially harmful to the fetus and infant. This report analyzes trends and current patterns of newborn and infant health in San Luis Obispo County, compared to the state of California. Results show that county rates have shifted from below to above the state:
Infant Deaths. Before Diablo Canyon opened (1968-1984), the county death rate under one year was 16% below the state. Most recently (2010-2024), the county was 1% above the state, including 11% and 23% higher for white non-Hispanics and white Hispanics.
Premature Births. In the earliest period available (1995-1999), the county rate of premature births (<36 weeks gestation) was 21% below the state. Most recently (2020-2024), the rate was 3% above the state (8% and 31% higher for white non-Hispanics and white Hispanics).
Birth Defects. In the period 2016-2024, the county rate of 12 types of birth defects was 114% greater than (more than double) the state, 3rd highest among the 35 largest California counties.
Other Newborn Health Measures. In addition, the county also has higher current (2016-2024) rates of common newborn risk factors, including those requiring assisted ventilation, those with low five-minute Apgar scores (a measure of infant health), and newborns transferred to another facility.
Child Cancer. Child cancer is believed to often be an adverse outcome that began in pregnancy. Early in Diablo Canyon’s operation (1988-1992), county cancer incidence 0-19 was 26% below the state; in the 30 years since then (1993-2022), the county rate was just 2% below the state.
No explanation for these findings is apparent, as risk factors in the county are not elevated. Compared to the state, the county has low rates of minorities, uninsured, foreign born, and languages other than English spoken at home; and similar rates of income, education, and poverty. The county rate of the most common maternal birth risk factors are below the state (overweight/obese mothers, mothers <20 or >35, mothers on WIC or Medicaid, and previous Cesarean section).
Further review of county health patterns is warranted to assess what role exposures to radioactivity from Diablo Canyon has played in these trends. Results should be made available to officials and the public. No major decision on the future of the plant should be made without a thorough understanding of the impact exposures have had on local health………………………………………………………………………………………………………………………………………………………………………………………………………………………………https://radiation.org/wp-content/uploads/2026/04/Diablo-Canyon-report-November-2025.pdf
Forty years ago, a nuclear disaster struck Chernobyl. Women from Rivne Nuclear Power Plant were sent to cook for clean-up crews. They faced radiation and health problems. Food meant for workers was often wasted or contaminated. Some food was smuggled out. Decades later, these women fight for promised pensions. Their experiences offer insight into the disaster’s lasting impact.
When Raya heard of a nuclear power plant accident, she turned to Ukraine’s Rivne Nuclear Power Plant close by: “We looked at our gherkin barrels — that’s what we call our power plant chimneys — and we could see there was nothing wrong with them.” But then the truth emerged: The accident was at their sister plant in Chernobyl, 180 miles east, and Raya had to go there to cook.
It has been 40 years since the world’s worst nuclear disaster and so much has been written and filmed about Chernobyl. But Polish writer Witold Szablowski found a little-known story for his book What’s Cooking in the Kremlin, a history of Russia through food. Szablowski knew how, even in the worst disasters, those working to save the situation had to eat, so someone had to cook for them. He found seven women alive, out of a group of 15 sent from Rivne after the disaster.
All the women suffered health issues, though not being in the actual plant spared them a bit. Dosimeters, to measure radiation, were placed at the entrance of the canteen, and when clean-up workers came from the plant, their buzzing became frantic and continuous. “It was a dreadful sound,” recalled Valentina, the head of the group.
Finally, the dosimeters were removed. Why remind people about radiation, when nothing could be done? The countryside around Chernobyl was abandoned. Raya recalled cows “mooing pitifully, because the people had been taken away and there was no one to milk them”. The canteen had also been abandoned. An earlier group of cooks were so terrified, they fled through the forest. That act had probably sealed their death warrants since Chernobyl’s forest was one of the worstaffected areas.
Food shortages were the norm in the latter days of the Soviet Union, but a guilty state ensured Chernobyl’s workers were given the best meats, dairy and fruit from across the country. “There was a whole sea of produce there,” Luba, another cook, recalled. “Little cubes of butter, full-fat cream — it sounds funny, but in those days, under Gorbachev, that was a real delicacy.” Workers had to drink glasses of cream, perhaps in the hope that its calcium would counter the depletion in their bones ..
Yet this food, which would normally have been the stuff of fantasies for people, was mostly wasted. Workers just wanted fruit juices and vodka. “They were burning up Witold. Burning up from inside,” Olga said. It was hard for the cooks to see such food disregarded. By habit, Luba would tell workers to take chocolate and give it to a kid, if they didn’t want it for themselves. Then she realised the food was contaminated by just being there, and no kid should have it.
Inevitably, some food was smuggled out. In Nobel Prize winner Svetlana Alexievich’s Voices from Chernobyl , one woman tells her how, in the months of fear afterwards, she only bought the most expensive meats to be safe: “Then we found out it was the expensive salami that they mixed contaminated meat into, thinking, well, since it was expensive, fewer people would buy it.” It is almost grimly comic how quickly the usual compromises and corruptions of life reasserted themselves.
Decades later, Valentina is fighting for the special pensions they were promised. An agent says she’ll arrange it for a thousand dollars — and tells an outraged Valentina that it’s a discount: “She charged those who hadn’t been in Chernobyl several thousand.”
Chernobyl’s 40th anniversary has been marked by articles lamenting how it set back nuclear power for decades. Sam Dumitriu, a British policy analyst, notes with some puzzlement that polls show women are far less likely to support nuc ..
The Scottish Campaign to Resist the Atomic Menace has issued a reminder of the huge human cost of the Chornobyl disaster in Ukraine to mark its 40th anniversary this Sunday, 26th April. Studies indicate a result of the disaster of between 16000 and 40000 fatal cancers. Others claim these estimates are very conservative.(1,2)
Pete Roche of SCRAM said: “The contrast between what happened 40 years ago in Ukraine at the Chornobyl nuclear plant – and the proclamations of today’s nuclear industry that it is not dangerous or dirty – could not be greater. Chornobyl contamination was widespread across Europe and is estimated to result in anything between 16,000 and 40,000 fatal cancers, possibly many more.
“Whilst we haven’t experienced a full meltdown at a UK nuclear plant to date, the industry’s record in the UK is not a clean one. These include the serious 3-day reactor core fire at Windscale in Cumbria in 1957 and other accidental releases of highly radioactive material into the sea and the local environment, and in Scotland the waste shaft explosion at Dounreay in 1977.
“Both Torness and Hunterston power stations in Scotland suffered significant cracking in their graphite reactor cores over time, and there have been numerous shut downs over their years of operation but thankfully did not result in the type of full scale regional emergency at Chornobyl or in Japan at the Fukushima plant in 2011. The inherent danger is there despite nuclear public relations efforts, and the legacy of toxic waste will be with future generations for hundreds of years. 40 years after the disaster, it is still highly vulnerable from the conflict in the region. Wind turbines, hydro plants and solar panels don’t carry these risks.
“After the reprocessing at Sellafield was abandoned, highly radioactive reactor fuel elements will now be stored on UK nuclear sites well into the 2100s. No safe solution has been found other than looking for eventual deep burial at a location yet to be determined, that will need guarded for hundreds if not thousands of years.
“On the positive side of the debate over energy, with Scotland’s huge renewable resources, nuclear is not needed. Scotland can power itself, and export clean, green power to other countries – and combine that with energy storage, flexible green power and an upgraded grid system. The revolution in renewable energy is already well underway and is globally unstoppable. New nuclear power has no place in a clean, green energy system, and certainly not in Scotland.”
A recent Survation poll of 2000 people, indicated that a majority of Scots preferred renewable energy over nuclear to tackle the climate crisis and be most effective at reducing energy bills. It also found that the nuclear industry was the least trusted to ‘tell the truth aboutits products, costs, pollutants and safety record.’ (3)
The campaign group says nuclear is not needed and is an expensive distraction that will do nothing to tackle the climate crisis, calling instead for a 100% renewable energy system to be committed to by the next Scottish Government after the May election.
CAIRO, Egypt, Apr 23 2026 (IPS) – Six weeks into the 2026 Middle East military escalation, UNFPA Arab States Regional Office warns that its impact on 161 million women and girls living in conflict-affected areas across the region remain largely invisible in conflict analysis, humanitarian response, and funding priorities.
“The omission is not merely analytical – it is structural,” the report states. Without sex-disaggregated data and gender perspectives, the international community is conducting incomplete risk assessments, misaligning interventions, and missing critical opportunities for stabilization and peace.
The conflict is projected to cost regional economies $120–194 billion – equivalent to 3.7 to 6 percent of collective GDP. Four million additional people are estimated to be pushed into poverty and 3.64 million jobs may be lost. Women – overrepresented in informal employment – face disproportionate livelihood collapse while shouldering increased unpaid care work.
Supply chain shocks through the Strait of Hormuz threaten to delay lifesaving humanitarian supplies by up to six months. Across Gaza, Lebanon, Sudan, and Yemen, more than 260 health facilities and 14 mobile medical units have already shut down. Food insecurity is intensifying, with documented patterns showing women and girls eat last and least.
The report also highlights a surge in GBV risks driven by hyper-displacement, while sanctions and financial “de-risking” are crippling the ability of women-led organizations to deliver essential services. These organizations—often the first responders in crises—are being cut off from the very funding streams meant to sustain them
UNFPA is calling on national governments, UN agencies, donors, and civil society to:
Integrate gender systematically into all conflict analysis and response frameworks
Protect and fund GBV and sexual and reproductive health services as core, lifesaving interventions.
Finance and empower local women-led organizations, removing barriers to their access and participation.
Ensure women’s leadership in recovery, peacebuilding, and decision-making processes.
“Making women and girls visible is not optional,” the report concludes. “It is fundamental to effective humanitarian action, sustainable recovery, and lasting peace.”
UNFPA is the United Nations sexual and reproductive health agency.
By Mike Treen, GPJA, Global Peace and Justice, AOTEAROA, 5 April 26
Since the Cuban revolution triumphed on January 1, 1959, Cuba has initiated a medical revolution as part of the social revolution. As Wikipedia noted:
The new Cuban government stated that universal healthcare would become a priority of state planning. In 1960 revolutionary and physician Che Guevara outlined his aims for the future of Cuban healthcare in an essay entitled On Revolutionary Medicine, stating: “The work that today is entrusted to the Ministry of Health and similar organizations is to provide public health services for the greatest possible number of persons, institute a program of preventive medicine, and orient the public to the performance of hygienic practices.”[15] These aims were hampered almost immediately by an exodus of almost half of Cuba’s physicians to the United States, leaving the country with only 3,000 doctors and 16 professors in the University of Havana’s medical college.
The Cuban leaders ordered new medical schools to be built to train the doctors needed to replace those who left with doctors who adhered less to the mercenary spirit of the leavers. The doctor-resident ratio increased six-fold by the late 1990s. Cuba has three times the rate of the US, UK or New Zealand – 9 per 1000 compared to 2.5 for the US and UK and 3.5 for New Zealand.
By 2012, infant mortality had dropped to 4.8 per 1,000 live births compared to 6 for the US. Life expectancy is one year less that the US (although it exceeded the US briefly during Covid). Cuba’s GDP per capita is one tenth of the US when measured in US dollars.
“Since 1960, some 600,000 Cuban medical professionals have provided free health care in over 180 countries. The government of Cuba has assumed the lion’s share of the cost of its medical internationalism, a huge contribution to the Global South, particularly given the impact of the US blockade and Cuba’s own development challenges. ‘Some will wonder how it is possible that a small country with few resources can carry out a task of this magnitude in fields as decisive as education and health,’ noted Fidel Castro in 2008.”
Cuba has also helped train doctors from across the globe at no cost to the tens of thousands given scholarships. Helen Yaffe writes: “In the 1960s, it began training foreigners in their own countries when suitable facilities were available, or in Cuba when they were not. By 2016, 73,848 foreign students from eighty-five countries had graduated in Cuba while that nation was running twelve medical schools overseas, mostly in Africa, where over 54,000 students were enrolled. In 1999, the Latin American School of Medicine (ELAM), the world’s largest medical school, was established in Havana. By 2019, ELAM had graduated 29,000 doctors from 105 countries (including the United States) representing 100 ethnic groups. Half were women, and 75 percent from worker or campesino families.”
There are currently 20,000 Cuban doctors working in 50 countries. The US NPR reported March 24, 2026, that the U.S. also recently passed a law allowing it to impose sanctions on countries that work with Cuban doctors.
“The countries that have broken off these contracts are afraid. They are afraid of retaliation by the United States,” says William LeoGrande, a professor of government in the School of Public Affairs at American University. “This is typical of Donald Trump’s foreign policy, which is based essentially on coercive diplomacy: ‘Do it our way, or else.’ So: ‘Get rid of the Cuban doctors, or else.’ ”
Sanctions deepened in 2019 by US President Trump
The deepening of sanctions since 2019 has resulted in the first deterioration of health statistics in Cuba ever. Even during the very difficult period in the early 1990s when the Soviet Unon collapsed and Cuba lost 90% of its trade partners and GDP declined 25%, they were able to maintain progress on health care. That is not the case today. The fuel blockade has resulted in blackouts that prevent medical institutions from functioning. Infant mortality is increasing. Life expectancy is declining.
Cuba’s downward spiral accelerated in January, after the U.S. capture of Venezuelan President Nicolás Maduro choked off oil from Cuba’s main benefactor. (As Science went to press, the U.S. signaled it would allow a Russian tanker full of crude oil to reach Cuba this week.) The U.S. government hopes the crisis will finally dislodge the island’s Communist regime. “I do believe I will have the honor of taking Cuba,” U.S. President Donald Trump told journalists this month. Cuba’s science is collateral damage. “There’s an effort to degrade everything Cuba has achieved in education and science, and send us back to the Stone Age,” says Mitchell Valdés Sosa, director of the Cuban Neurosciences Center.
Nationwide electricity blackouts lasting 20 or more hours a day are forcing doctors to triage care and putting lives at risk. At the Hermanos Ameijeiras Hospital in Havana, “we receive the most complex neurosurgical cases in the country,” says neurosurgeon Marlon Manuel Ortiz Machín. “Surgeries must not stop; it’s sometimes a patient’s last chance.” Yet he’s been “caught in the dark” during complex operations. “All you can do is pray until the generator comes back on.”
Gail Reed, a volunteer for the U.S. nonprofit MEDICC who was in Havana last week, fears Cuba’s medical system is on the brink of collapse. “Hospitals are running out of supplies. It’s heartbreaking and unconscionable,” she says. With Cuba’s infant mortality rate rising, MEDICC is “trying to protect women with high-risk pregnancies” by installing solar panels in maternity homes, Reed says.
“We’re seeing malnourishment, people losing weight,” says Angela Garcia, executive director of Global Links, a Pittsburgh-based nonprofit. Flying into Havana last month, she says, “the first thing I noticed was an acrid odor”—from burning mounds of trash that has gone uncollected because of fuel shortages.
Damage to Cuba’s vaunted biotech sector could have an outsize impact on health and the economy. The 51 enterprises that make up BioCubaFarma, a government entity, produce scores of drugs, vaccines, and reagents, many of which are exported to 77 countries. One high-profile compound is CIMAvax-EGF, an immunotherapy against lung cancer that had positive results in early clinical trials in the U.S., done in partnership with the Roswell Park Comprehensive Cancer Center in Buffalo, New York.…………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………..
Cuba’s role fighting the Ebola crisis………………………………………………………………………………………………………………………………………………………………
Cuba’s role in training doctors for Timor Leste and many Pacific Islands
Unknown to most of us in this part of the world, Cuba is also providing doctors and training locals in most of the Pacific Island states in a special medical school in Cuba, The Latin American School of Medicine. The Australian Development Policy Centre blog reported in February 2012: (https://devpolicy.org/cuba-in-the-pacific-more-than-rum-and-coke-2-20120224/):………………………………………………………………………………………………………………………………………………………………………………………………………………………
Cuba has also run a programme over the last two decades that has cured millions of people of functional blindness. It is very similar to great programme established by the late New Zealand doctor Professor Fred Hollows who was a renowned New Zealand-born eye surgeon who dedicated his life to restoring sight. A good socialist himself, he was horrified at the neglect that Aboriginal Australians in particur were forced to endure. The Fred Hollows Foundation NZ continues his legacy by fighting to end avoidable blindness in the Pacific region, training local eye care specialists, and conducting thousands of sight-restoring surgeries.
Set in motion on July 8, 2004, Operation Miracle took shape within the context of the Bolivarian Alliance for the Peoples of Our America – otherwise known as ALBA – which Cuba and Venezuela established that year also.
In 2019, Cuba was itself hit by the Covid crisis and had to invent three vaccines to treat itself and achieved the same 90% effectiveness as the Western drugs they were not allowed to get. Cuba has also developed advanced medical sciences and hundreds of patented drugs that we can’t access. This includes treatments for Dementia, Cancer, and Polio that would be very welcome in our own communities which suffer significantly from these ailments. My own brother has dementia and look at what Cuba has achieved here. U.S. Citizens in Cuba for New Breakthrough Alzheimer’s Treatment
But the lockdowns saw a collapse in tourism to Cuba, which was their main foreign currency earner. The newly elected US President Trump also imposed new extreme sanctions, which were maintained by President Biden despite promises to remove them during the election period. When Trump returned in 2025, Cuba was subjected to a renewed and even more extreme embargo from the US empire (including fuel). This has led to very harsh conditions in Cuba and a collapse in their ability to deliver the same medical internationalism as before, including for the Pacific.
Working people worldwide need to take our own lessons from the Ebola, Covid, and similar health crises facing the world. Public health should be promoted and available to everyone on Earth. Ebola and Covid demonstrated that neglect of the Earth and its people anywhere will ultimately be a threat to human survival everywhere. Putting profits before people is a dead end, literally. The monopoly control over drugs and other aspects of medical research by the drug companies needs to be broken. Finding an alternative way of running this world which puts people and the planet before profit also must involve defending Cuba and its revolutionary example.
The world owes a giant debt to Cuba. The Nuestra America solidarity convoys are an example of what needs to be done until Cuba is free of all threats. What we can be sure of is that Cuba will not surrender despite the hardship they face. Hundreds of thousands will fight if invaded. Cuba’s most famous singer, 79-year-old Silvio Rodriguez, volunteered to fight and demanded an AK47 which was delivered by the Cuban President. This week, fuel has arrived on a Russian ship despite threats. More will come as the world increasingly wins its freedom from the US empire and its domination. That empire is declining and nations are asserting their independence as best they can. Some (like Cuba, Iran, Palestine, Lebanon, Venezuela) are fighting for their survival and we must fight side by side with them for the future of humanity and the planet. The empire’s alternative is permanent war and economic collapse. Peace with justice comes when we defeat that empire once and for all. https://gpja.org.nz/2026/04/05/cuba-has-saved-millions-of-lives-across-the-world-we-must-fight-for-its-survival-as-a-duty-to-humanity/
“…………………………………………………………………………………… The Fukushima Daiichi nuclear plant, built by General Electric (GE) in the mid-1960s, was designed to withstand natural disasters, but its creators never foresaw an earthquake like that. When the plant’s sensors detected the quake, its reactors automatically shut down. That emergency shutdown (or scram) halted its fission process, triggering backup power to keep cold seawater flowing through the reactors and spent-fuel containers to prevent overheating. Things at Fukushima were going according to plan until that massive tsunami battered the plant, washing away transmission towers and damaging electrical systems. There were backup generators in the basement, but those, too, had been inundated by waves of seawater, and an already bad situation was about to get far worse.
A power outage at a nuclear power plant is known as a “station blackout.” As you might imagine, it’s one of the worst scenarios any nuclear facility could possibly experience. If all electricity is lost, that means water is no longer being pumped into the reactor’s scalding-hot core to cool it down. And if that core isn’t constantly being cooled, one thing is certain: disaster will ensue. The fission process itself may be complicated, but that’s basic physics. To make matters worse, there were three operatingreactors at Fukushima Daiichi. Luckily, three others had already been shut down for maintenance. If power wasn’t restored in short order, that would mean that all three of Fukushima’s reactors were in very big trouble.
We would later learn that no one — not at TEPCO, GE, or among Japanese regulators — had ever considered the possibility that all the reactors might lose electricity at once. They had only drawn up plans for one reactor to go down, in which case the others could keep the plant running. But all of them offline, and every generator out of commission? There was no precedent or playbook for that.
The nuclear industry has a reasonably polite name for a disaster like the one that was rocking Fukushima. They refer to it as a “beyond design-basis accident” because no single nuclear plant design can account for every possible problem it might encounter in its lifetime. The fact that there’s a term for this should make you anxious.
Meltdowns and Fallout
Over the next several days, the emergency at Fukushima Daiichi only worsened. Every effort to restore power to its reactors hit a dead end. On-site radiation-detection equipment, which would have triggered warnings and guided evacuation efforts for those in danger, was no longer functioning. Plans to pump water into the reactors to cool them had faltered. Their cores kept overheating, and the boiling pools of spent fuel were at risk of drying out, potentially triggering a massive fire that would release extreme amounts of radiation.
Within three days, following a series of fires, hydrogen explosions, and panic among those aware of what was happening, Fukushima’s Units 1, 2, and 3 experienced full-scale core meltdowns. Over 150,000 people within an 18-mile radius had already been forced to evacuate, and radiation plumes would take two weeks to spread across the northern hemisphere, although the Japanese government wouldn’t admit publicly that any meltdown had occurred until June 2011, three months later.
The only good news for the 13 million people living 150 miles south in Tokyo was that, during and immediately after the meltdowns, prevailing winds carried much of Fukushima’s radioactive material away from the smoldering reactors and out to sea. It’s estimated that 80% of the fallout from Fukushima ended up in the ocean, meaning most of it headed east rather than toward population centers to the south and west. The other fortunate news was that the spent fuel containers had somehow survived it all. If their water levels in the pools had been drained, far more radiation would have been released.
But Tokyo wasn’t completely spared. After years of research, scientists discovered that cesium-rich microparticles had blanketed the greater Tokyo area, an unpopular discovery that drew backlash and threats of academic censorship. Areas around the Fukushima exclusion zones recorded the highest radiation levels. Japanese government officials continually downplayed the dangers of the accident and were reluctant to even classify the event as a Level 7 nuclear disaster, the highest rating on the International Nuclear Event Scale, which would have placed it on a par with the 1986 Chernobyl nuclear disaster. Japanese officials have also failed to conduct long-term epidemiological studies that would include baseline measurements of cancer rates, which has cast doubt on thyroid screenings that found troubling incidents of cancer far higher than researchers expected.
Radioactive Fish
Prior to the earthquake, the ocean’s cesium-137 levels near Fukushima were 2 Becquerels (a unit of radioactivity) per cubic meter, well below the recommended drinking water threshold of 10,000 Becquerels. Just after March 11, 2011, cesium-137 levels there spiked to fifty million before decreasing as sea currents dispersed the radioactive particles away from the coast. The ocean, however, had been poisoned.
In the years that followed the Fukushima nuclear disaster, researchers documented a frightening, yet predictable trend. Radioactive isotopes in seawater were taken up by marine plants (phytoplankton), which then moved up the food chain into tiny marine animals (zooplankton) and, eventually, to fish.
Cesium-137 consumed by fish can reside in their bodies for months, while Strontium-90 remains in their bones for years. If humans then eat such fish, they will also be exposed to those radioactive particles. The more contaminated fish they eat, the greater the radioactive buildup will be.
In 2023, over a decade after the incident, radiation levels remained sky-high in black rockfish caught off the Fukushima coast. Other bottom-dwelling species have been found to be laden with radioactivity, too, including eel and rock trout. Further concerns have been raised about the treated radioactive water that TEPCO continued to release into the ocean, prompting China to suspend seafood imports from Japan. Aside from those findings, there have been very few studies examining the effects of Fukushima’s radiation on ecosystems or on the people of Japan.
“Japan has clamped down on scientific efforts to study the nuclear catastrophe,” claims pediatrician Alex Rosen of International Physicians for the Prevention of Nuclear War. “There is hardly any literature, any publicized research, on the health effects on humans, and those that are published come from a small group of researchers at Fukushima Medical University.”
Recognizing such levels of radiation, even if confined to the waters near Fukushima, would cast the country’s nuclear industry as a significant threat — not only to Japan but globally. Any admission that Fukushima’s radiation is linked to increased cancer rates would raise broader concerns about nuclear power’s future viability. Radiation exposure is cumulative and, although Fukushima didn’t immediately cause mass casualties, it wasn’t a benign accident either. It took decades before it was accepted that Chernobyl had caused tens of thousands of excess cancer deaths. It may take even longer to completely understand Fukushima’s full effects. In the meantime, the still ongoing cleanup of the burned-out facilities may cost as much as 80 trillion yen ($500 billion).
It’s been 15 years since Fukushima’s reactors experienced those meltdowns and we still don’t fully understand their long-term repercussions. Nuclear power advocates will argue that Fukushima wasn’t a serious incident and that nuclear technology is still safe. They’ll minimize radiation threats, remain optimistic that new reactor designs will never falter, dismiss the fact that there’s simply no permanent solution for radioactive waste, and overlook the inseparable connection between nuclear power and atomic weapons. After all, among other things, we’ll undoubtedly need nuclear energy to help power the artificial intelligence craze, right?………………………………………………………………………………………………………………………………………………………………………. With nine nuclear-armed nations and roughly 12,000 nuclear warheads on this planet, worries about nuclear war are unavoidable. However, the danger of a nuclear disaster at a seemingly “peaceful” nuclear facility is often ignored. The future of atomic energy remains uncertain, but it is our duty to eliminate this hazardous energy source before another Fukushima triggers a war-like catastrophe all its own.mhttps://scheerpost.com/2026/03/20/searching-for-solace-in-a-nuclearized-world/
When a hypothesis is at odds with data, you don’t discard the data – you modify the hypothesis.
Medical data trump hypothetical estimates of “radiation doses” that are disconnected from reality, not measured nor even measurable.
Internal exposures to alpha emitters like plutonium and pure beta emitters like tritium and carbon-14 are notoriously difficult to measure, especially when it comes to pregnant women and their developing fetuses.Too often, medical data have been mistrusted or even discarded because the estimated radiation doses were “too low” to account for the harmful effects recorded
This happened in the aftermath of the TMI nuclear accident, for example, and following the German KiKK study that found significantly increased leukaemia in children under 5 within 5 kilometres of any one of Germany’s then-operating 17 nuclear power reactors.All 17 reactors are now shut down, as Germany has completely phased out of nuclear power.
——————————————————————————–
‘Robust and consistent’ signal: Cancer mortality rates higher near nuclear power plants
By Mark Leiser, Fact checked by Heather Bile, Healio, March 16, 2026
[from Hematology/Oncology News Today]
Key Takeaways
An analysis of every U.S. county showed higher cancer mortality rates in those located closer to nuclear power plants.
The findings cannot prove causality but warrant further investigation, researchers concluded.
U.S. counties located closer to nuclear power plants have higher cancer mortality rates than those located farther away, results of a national analysis showed.
The study — which accounted for environmental, socioeconomic and other factors — yielded results that remained consistent through multiple sensitivity analyses.
During the 19 year study period, researchers estimated that 115,586 cancer deaths nationwide could be attributed to nuclear power plant proximity.
Data derived from Alwadi A, et al. Nat Commun. 2026;doi:10.1038/s41467-026-69285-4.
In light of increased attention on nuclear power as a low-carbon energy alternative, more research into its potential effects on public health is warranted, according to Yazan Alwadi, PhD, postdoctoral research fellow in the department of environmental health at Harvard T.H. Chan School of Public Health.
“We want to be very clear that we cannot prove causality. However, the signal we observed is very robust and consistent, and it is surprising it has not been shown before,” Alwadi told Healio. “In my opinion, we have all the evidence we need to justify going to the next level of investigation.”
Impact of ‘normal operation’
A majority of studies that examined the effects of routine operation assessed cancer incidence or mortality in a specific region located near one or two plants. The limited setting reduces the statistical power to detect effects, he said.
Alwadi and colleagues launched their study after local public health officials in Plymouth County, Massachusetts — where the now-closed Pilgrim Nuclear Power Station is located — asked them to evaluate what they considered concerning cancer patterns in the region.
“Rather than focusing on a single county, we felt it was scientifically stronger to conduct a national analysis,” Alwadi said.
The researchers used U.S. Energy Information Administration records to identify the locations and operational dates of all nuclear power plants located within 200 km — about 124 miles — from the center of any U.S. county. They obtained county-level cancer mortality data from the CDC, focusing on the period between 2000 and 2018.
Alwadi and colleagues employed what they described as a “spatially resolved, inverse distance-weighted proximity metric.”
They used statistical modeling to calculate cumulative effects of multiple nearby nuclear power plants on people aged 35 years or older, controlling for potential confounders — such as BMI, smoking prevalence, household income and educational attainment — in each county.
A positive association
The results revealed a positive association between proximity to nuclear power plants and cancer mortality.
Investigators estimated 115,586 cancer deaths (95% CI, 56,964-173,326) during the 19-year study period — or approximately 6,400 per year across the country — could be attributed to nuclear power plant proximity.
For men and women in most age groups, results showed considerably higher relative risks when equivalent plant distance was 50 km or less, with risk curves beginning to plateau with greater distance.
Relative risk estimates were lowest among the 35-to-44 age group for both women and men, then began to increase with age.
Among women, those aged 55 to 64 years exhibited the highest relative risk (RR = 1.19), with 2.1% (95% CI, 1.3%-2.9%) of cancer deaths in that age group attributable to nuclear power plant proximity.
Among men, those aged 65 to 74 years had the highest relative risk (RR = 1.2), with an estimated 2% (95% CI, 1.2%-2.7%) of cancer deaths in that age group attributable to nuclear power plant proximity.
Overall results showed the highest attributable cancer mortality burden among individuals aged 65 to 84 years. Researchers estimated 4,266 deaths (95% CI, 3,000-9,112) per year among those aged 65 or older to be attributable to proximity to nuclear power plants.
The associations between proximity and cancer mortality persisted in multiple sensitivity analyses, Alwadi said. In one, researchers adjusted the distance from nuclear power plants to county centers, changing by increments of 10 km until it reached a 100-km radius. In another, investigators varied the average proximity window across five intervals, ranging from 2 years to 20 years.
The consistency of the results demonstrate that they “are not driven by arbitrary choices in model variables or parameters,” the researchers wrote.
The investigators acknowledged study limitations.
The analysis assumed equal impact of all nuclear power plants rather than incorporating direct radiation measurements, and it assessed all malignancies combined even though radiation sensitivities and latency periods vary by cancer type.
Also, the standard formula investigators used to calculate attributable fraction assumes a causal relationship between the outcome and exposure without accounting for potential exposure misclassification or residual confounding.
‘We need to dig deeper’
The study is the first to the authors’ knowledge that uses a continuous proximity metric to examine nuclear power plant proximity and cancer mortality on a national level.
The use of 19 years of national cancer mortality data and a 10-year average nuclear power plant proximity window allowed for a “robust temporal assessment” of proximity’s long-term effects, the researchers wrote.
However, the findings have been the subject of some public criticism.
The Breakthrough Institute — a California-based research center that seeks to identify technological solutions to environmental challenges — published a post on its website challenging the accuracy of the paper, as well as another that Alwadi’s research group previously published that showed an association between residential proximity to nuclear power plants and elevated cancer incidence among people in Massachusetts.
The Breakthrough Institute — a California-based research center that seeks to identify technological solutions to environmental challenges — published a post on its website challenging the accuracy of the paper, as well as another that Alwadi’s research group previously published that showed an association between residential proximity to nuclear power plants and elevated cancer incidence among people in Massachusetts.
“The two papers make the fundamental mistake of confusing correlation with causation,” the online post reads.
The post authors point to the lack of a control group in the Massachusetts state-level analysis and use of “an improperly sampled group” in the national study. Distance from a nuclear plant is not a substitute measure of radiation dose, they argued, noting factors such as wind direction, shielding or monitored emissions had not been taken into account. Researchers also could not demonstrate that people who live nearby receive “any incremental dose beyond natural background radiation,” they added.
Consequently, the research is “fundamentally dangerous” and increases public health risks by “fueling efforts” to close existing nuclear plants and prevent new ones from coming online, the post authors wrote, suggesting this would compound the health risks associated with fossil-fueled electricity generation.
Alwadi said he is aware of the criticisms but believes many of them result from “lack of knowledge of statistics or epidemiology.”
Many of the concerns expressed in the online post already have been acknowledged by researchers in the manuscript as study limitations or addressed in sensitivity analyses performed to answer questions raised by peer reviewers prior to publication, Alwadi said. The methodology “has been put through the wringer and checked step by step,” he added.
“Anyone can write what they want on their own website,” Alwadi said. “If they have a legitimate criticism, they can submit it to the journal. If the editors determine it is valid, we would have to respond to it. We haven’t received anything like that.
“We have, however, received emails from so many people asking to collaborate with us or to investigate this more closely in specific regions,” Alwadi added. “People are very interested in this. They want to know if there is an effect. We want to know, too.”
Alwadi and colleagues are continuing to analyze additional datasets and perform cohort analyses. They have hypotheses that they hope will serve as the foundation for exposure pathway-specific analyses. Alwadi also emphasized the need for additional research into latency effects and impacts on risks for specific malignancies.
“The best data we get comes from randomized clinical trials, but that design is not applicable to the study of environmental exposures,” Alwadi said.
“Epidemiological studies progress in stages. If you find a signal, you keep going. We certainly did not want to see an effect, but we observed a systematic association that is robust to sensitivity analyses and observed across multiple datasets and geographic aggregations.
“We acknowledge that does not establish causality,” he added. “But what if you lived in a town and noticed that everybody who drank from a specific well got sick? If you didn’t know the exact mechanism, would you still drink from that well or would you investigate it? That’s all we’re saying. We need to dig deeper.”
1. Today saw release of a report prepared for the US Department of Energy that will, alongside others from US agencies like OSHA, be feeding into the US NRC review of radiation Protection Standards mandated by the Trump Directive (EO 24300) issued in May last year. The NRC draft of revised regulations on Radiation Safety is expected 30 April 2026. The attached report to the US DoE – with particular significance for radiation safety for workers in and populations living close to nuclear power reactors – gives a clear indication of how this process is likely to result in significant weakening of protection standards
In summary it advocates
abandoning the Linear No Threshold and As low as Reasonably Achievable principles that offer some protection at low levels of exposure based on the principle that there is no safe level of exposure
resetting the annual occupational exposure limit to 100 mSv – a doubling of the current US standard of 50mSv and a five-fold increase in the 20mSv annual occupational standard that applies in most other countries including Australia
raising the public exposure limit from 1 mSv to 5 mSv
I think we can expect other US agencies to submit similar reports
2. As previous posts on this issue have noted these proposals to weaken radiation protection for workers and the public come at a time when the evidence is mounting from studies of workers and communities exposed to radiation releases in and from Nuclear power pants for a revision that would tighten the current standards. Today saw the release of a new book by Ian Fairlie – The Dangers of Ionising Radiation: A Scientific Guide to Radiation Risks for Government Agencies, Legal Professionals and Medical Clinicians has just been published (Ethics International Press. 2026) https://ethicspress.com/products/the-dangers-of-ionising-radiationAs anticipated this updates much of the earlier work in Ian Fairlie and Cindy Folkers book –
The Navajo Nation – a 27,000-square-mile piece of land that overlaps with parts of Arizona, New Mexico, and Utah – has more than 500 abandoned uranium mines that have been identified by the EPA.
‘The government was mining this uranium for the nuclear program, for nuclear weapons, and they put national security and having easy, inexpensive access to uranium ahead of the interests of the health and well-being of the people living there
Teracita Keyanna’s youngest son was born with a hole in his heart after she spent decades living in a uranium-contaminated Navajo community in New Mexico.
Kravin Keyanna, now 19, spent the first decade of his life dealing with a severely weakened immune system. He constantly got ear infections, his mother said, which led to him having sensitive hearing.
‘We spent a lot of time in the hospital because he was more sickly than most kids,’ Teracita told the Daily Mail. ‘Because of his immune system, they didn’t want to do surgery on him because they were afraid that it was going to cause more harm in the long run.’
After about 11 years, his heart closed up on its own and healed without surgical intervention.
Meanwhile, Teracita’s 11-year-old daughter, Katherine, has continued to develop abnormal tissue growths underneath her top layer of skin near her lymph nodes.
‘She’s had to have them removed. And so she has gone through four different surgeries in five different locations,’ Teracita said. ‘Her first surgery was when she was 3 years old and the latest one was last year at 10 years old.’
Kravin and Katherine spent years of their childhood living on Red Water Pond Road, a Navajo settlement less than two miles away from the New Mexico border. Their family home was sandwiched between three abandoned uranium mines that remain highly toxic to this day.
These mines were part of a Cold War-era uranium boom that helped build America’s nuclear arsenal. Extraordinarily high levels of radiation from hundreds of long-forgotten sites in the Navajo Nation have exposed generations of Native American families to elevated health risks, including cancer and other unknown ailments.
Teracita was born in 1981 and has spent the majority of her life in the Red Water Pond Road community. Uranium ore extraction continued in the area until 1986 at the two nearby mining sites owned by Quivira Mining.
Mining at the United Nuclear Corporation-owned Northeast Church Rock Mine, immediately south of her ancestral home, lasted until 1982.
‘When I was young, nobody ever told me personally about the dangers of uranium,’ she said. ‘I didn’t know that the mines that were near my home were uranium mines. It was like living with a time bomb, and you didn’t even know that it was there.’
Doug Brugge, the chair of the Department of Public Health Sciences at the University of Connecticut School of Medicine, said Kravin and Katherine’s conditions cannot be definitively tied to uranium exposure. But he didn’t dismiss the possibility either.
Brugge led a project in the 1990s that interviewed Navajo uranium miners, many of whom developed lung cancer from the radon gas released when cutting into uranium ore.
The effects on them are ‘unequivocally well established,’ Brugge said. The effects on their wives, children and grandchildren are murkier and harder to pin down.
Brugge actually grew up in the Navajo Nation as one of the few white children among his peers. He left with his family when he was 14 and when he returned in his thirties to study the uranium issue, he heard many stories similar to Teracita’s.
‘The thing that has long bothered me is many people told us they didn’t know. They had no idea there was anything hazardous associated with this mining,’ he said. ‘A lot of them didn’t speak English. They had a limited education level. Their access to news and media was fairly limited.’
On top of a lack of communication from authorities about the dangers, Teracita said the mines near her did not have fences or barriers, which meant people and livestock could freely wander into contaminated areas.
n March 2024, the Environmental Protection Agency took soil samples from Church Rock No. 1, the nearest Quivira-owned mine to where Teracita lived.
Exposure to contaminated surface soil at and around the 44-acre site carried an estimated one-in-100 cancer risk — meaning one additional person out of every 100 exposed residents could develop cancer in their lifetime. About 30 families, including Teracita’s, lived near the mine as of 2006, according to the EPA.
Brugge said that level of risk is ‘really high’ and pointed out that the EPA is usually already concerned if it’s at one in 100,000 or one in a million.
Teracita also lived half a mile away from the Church Rock uranium mill, also owned by United Nuclear Corporation. Facilities like this can extract uranium from mined rock to produce a powder called ‘yellowcake’.
This material can later be converted for use as fuel in nuclear power plants or, at higher enrichment levels, in nuclear weapons. The process is not entirely clean, however, as it also produces sandy-looking radioactive waste called ‘mill tailings’.
In 1979, two years before Teracita was born, the Church Rock uranium mill had a catastrophic spill that sent 1,100 tons of mill tailings and 93 million gallons of radioactive wastewater into the Navajo Nation via the Puerco River.
There have not been extensive studies on the extent of the damage caused by this disaster, which to this day is considered the largest accidental release of radioactive material in US history.
While it is unknown how many people were possibly exposed and developed health conditions later in life, children who swam in the river or herded sheep across the water were left with serious burns on their skin.
Teracita said many of her neighbors and friends on Red Water Pond Road have mysteriously developed diabetes or cirrhosis of the liver without excessive drinking or smoking.
Teracita lived on Red Water Pond Road with her family until around 2018, when the EPA offered them financial assistance to move away while the agency cleaned up the mines. Prior to that, she had been exploring economically feasible ways to leave.
‘I was already trying to figure out what we could do for our kids in order to safeguard them further, considering that when I was a kid, nobody safeguarded me,’ she said.
The Department of Energy says there are a total of 4,225 uranium mines across the United States, the vast majority of them abandoned.
The Navajo Nation – a 27,000-square-mile piece of land that overlaps with parts of Arizona, New Mexico, and Utah – has more than 500 abandoned uranium mines that have been identified by the EPA.
This means the Navajo have just over 11 percent of the country’s abandoned mines within their borders, despite making up just 0.8 percent of America’s total landmass.
‘The government was mining this uranium for the nuclear program, for nuclear weapons, and they put national security and having easy, inexpensive access to uranium ahead of the interests of the health and well-being of the people living there” Brugge said.
It is not just the Navajo, who call themselves Diné in their language, who have been disproportionately exposed to the radioactive byproducts of mining operations, most of which ceased in the 1980s.
Nature Communications volume 17, Article number: 1560 (2026) , 23 February 2026 [Excellent graphics and tables]
Abstract
Understanding the potential health implications of living near nuclear power plants is important given the renewed interest in nuclear energy as a low-carbon power source. Here we show that U.S. counties located closer to operational nuclear power plants have higher cancer mortality rates than those farther away.
Using nationwide mortality data from 2000-2018, we assess long-term spatial patterns of cancer mortality in relation to proximity to nuclear facilities while accounting for socioeconomic, demographic, behavioral, environmental, and healthcare factors. Cancer mortality is higher across multiple age groups in both males and females, with the strongest associations among older adults, males aged 65–74 and females aged 55–64. While our findings cannot establish causality, they highlight the need for further research into potential exposure pathways, latency effects, and cancer-specific risks, emphasizing the importance of addressing these potentially substantial but overlooked risks to public health.
…………………………………………………………….Nuclear power plants emit radioactive pollutants that can disperse into the surrounding environment, leading to potential human exposure through inhalation, ingestion, and direct contact. These pollutants can be transported through air, water, and soil, contributing to long-term environmental contamination1. Populations residing near nuclear power plants may experience low-level chronic exposure to ionizing radiation via environmental release pathways. While our study does not include dosimetry, ionizing radiation is a well-established carcinogen2,3,4,5,6,7 and thus motivates investigation into proximity-based exposure patterns.
………………………Despite the importance and prevalence of nuclear power plants in the U.S., epidemiologic research regarding their health impacts remains rare. Most U.S. studies have focused on individual plants or limited regions, with only a few national assessments to date – many of which relied on fixed distance cutoffs to classify exposed populations8,9,11,12,19,21,22,23,24,25. These studies often focus on a single facility and its surrounding communities, which restricts their statistical power to detect effects and ability to capture broader exposure patterns. Furthermore, differences in study design, exposure assessment methods, and geographic scope make it difficult to draw generalizable conclusions.
In this work, we assess the association between county-level proximity to nuclear power plants and cancer mortality across the United States from 2000 to 2018. We find that counties located closer to operational nuclear power plants have higher cancer mortality rates, with stronger associations observed among older adults. These associations remain consistent across multiple sensitivity analyses and proximity definitions. The results highlight spatial patterns of cancer risk in relation to nuclear power generation and emphasize the importance of evaluating potential long-term health implications of nuclear energy infrastructure in population-scale studies…………………………………………………………………………………………………………………………………………………………………. https://www.nature.com/articles/s41467-026-69285-4